
|
In 2019 we discussed the basics of why patients wait a long time to hear back, get through on the phone lines, or be seen with a primary care doctor. Unfortunately, this problem seems to have worsened acutely with the COVID epidemic. As an update to that blog, we want to begin by highlighting again that according to Merritt Hawkins, the average wait time for a new patient appointment with a primary care doctor is 29 days, up 50% from 2014. In Rhode Island, the wait continues to be much longer. We’ve heard of patients quoted a six to twelve month wait period before they can see a doctor as a new patient!
As the COVID-19 situation in RI takes a turn for the worse (yet again) we find ourselves in a predicament as patients. The hospitals in RI are over 90% capacity for inpatient beds and ICUs are at more than 80%. This has been true on and off for a majority of the COVID pandemic. In states like FL, which are extremely hard hit right now, some ICUs and hospitals are unable to accept any patients. A nationwide news story recently revealed patients have died because they cannot get non-COVID-related hospital care when they need it and their local hospital is full.
Why am I telling you all this? Not because I am trying to scare you out of going to the hospital when you need it or to make you think all is lost. I am telling you this to emphasize NOW is a more important time than there ever was to get yourself a trusted Primary Care Doctor (PCP). PCPs can address your needs before you become very sick, can order testing as an outpatient to avoid waiting in the ER or urgent care, and we can help you identify illnesses and treat them quickly. The Direct Primary Care movement has picked up steam over the last seven years since we started Direct Doctors in RI. According to DPC Frontier, a site owned by a DPC physician/lawyer who was a founder of the movement, there are now over 1500 clinics doing pure Direct Care across the nation. There are likely many more than have been officially labeled on the map. Looking back to 2014, when we began, there were less than 100.
Direct Doctors will be celebrating our 7 year anniversary this August! Over that time, we’ve come to really appreciate the direct primary care model that we are using to deliver efficient, evidence based and personal care to our almost 1,000 patients. Like many of the other DPC practices across the country, we’ve noticed many benefits (for both the patient and physician), while also discovering a few barriers.
The two most common types of health insurances that we see today (outside of medicare and medicaid) are called PPOs and HMOs. 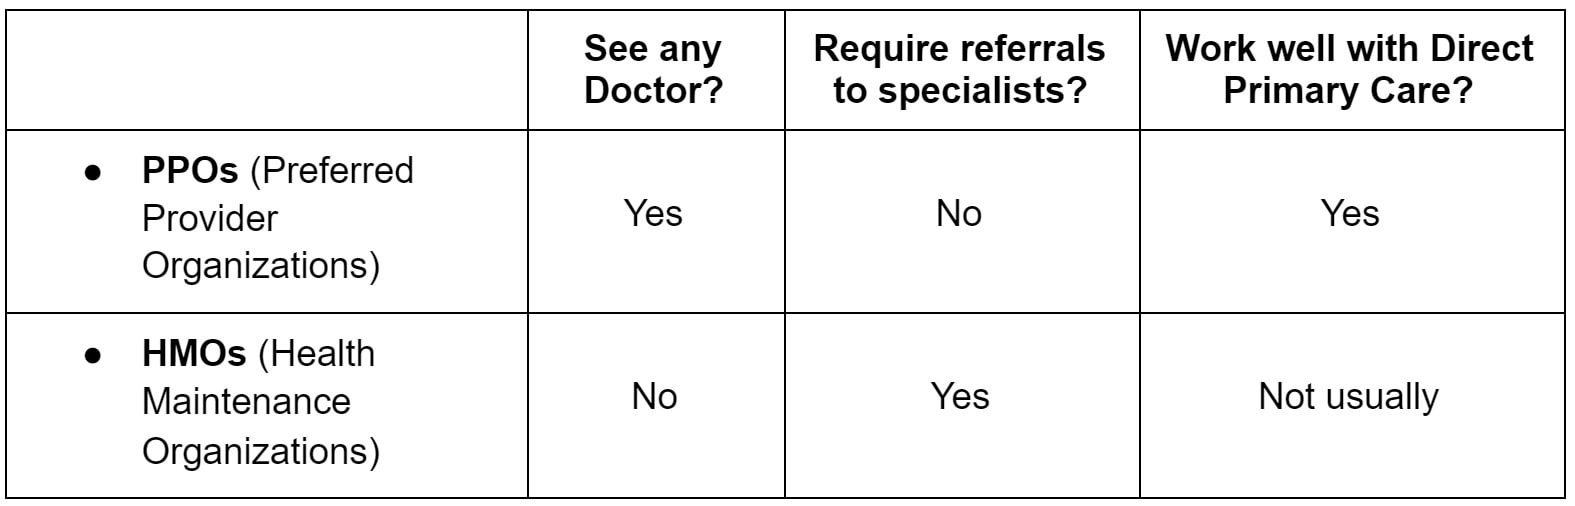 The majority of our blogs focus on the healthcare system in general, and how direct primary care can help fill in some of the gaps. Currently, I’d like to highlight some concerns with a more local healthcare issue that has been in the news lately. If you haven’t heard, the long anticipated merger between Lifespan and Care New England has been announced. This deal also involves Brown University who only noted the positive aspects of such a merger in their press release. The Providence Journal conversely, ran a much more balanced assessment article . Every time large health organizations merge or consolidate, the purported benefits are advertised far and wide: continuity of care will improve, costs will go down, quality of care will go up and the health ecosystem will dramatically change. In this case, we are told that all of Rhode Island will be better off with the two largest healthcare organizations combining powers to produce a health care utopia.... except all the data we have to date shows the exact opposite. We have mountains of evidence that whenever this happens, costs go up! When there is a monopoly on services and reduced choice for consumers, patients (or their insurers which eventually trickles down) end up getting charged more for the same services. There is evidence that the same thing happens when physician practices merge or get bought by larger organizations. You want more data? Here’s an article from 2018 showing that though hospital operating costs are reduced 15-30% by this kind of merger, costs still go up! And how about that “increase in patient care” that is touted. Here’s an article from Harvard just last year that indicates that hospital performance does not improve and patient satisfaction actually goes down. Interestingly, we do know that one of the only things that does decrease health care costs is access to good primary care. Neither Lifespan nor CNE have ever prioritized primary care, which is consistent among most large health care providers. What is the incentive for large hospitals to have great primary care that keeps patients away from their biggest revenue generators? Care New England allowed Memorial Hospital to close, displacing the main Family Medicine Residency in the state, which disproportionately affected the large minority population in the Pawtucket/Central Falls area (despite everyone's calls to improve health disparities). Brown Medical School, like many large academic institutions, loves to highlight their students who go into flashy specialties as opposed to holding those who love primary care in similar esteem. So those who are interested in primary care medicine are really exposed only to corporate medicine, PCMH and the types of practices we think need to be changed in the first place. Rhode Island, as a whole, already has a primary care shortage due to many factors which drives more patients to urgent care and ER facilities subsequently driving up costs for everyone. To combat this, these large organizations are turning more to mid-level providers (PAs and NPs) in their primary care setting. These providers historically order more tests, refer more to specialists, etc… which, you guessed it, also drive up costs. To assist with all of this “continuity,” these large organizations turn to bloated, insanely expensive, electronic medical record and billing software. Then to make up for these costs, primary care doctors are forced to see more patients, leaving little time for good medicine or pension for over prescribing, ordering and referring (as we’ve mentioned in the past) We do understand that there can certainly be an increase in academic research and improved specialty consultation within these institutions, so it’s not all bad. But in the end, the combination of poor primary care, hospital monopolies and the introduction of more HMO plans into the mix are setting our Rhode Island health care system up for increasing costs, decreasing patient choice without any change in outcomes or patient satisfaction. At Direct Doctors, we will continue to do our part in assisting patients with quality primary care access, lowering their medical costs and improving their overall care!  During the COVID pandemic, as many insurances started to see the necessity of telemedicine (i.e. video and telephone calls in place of in-person visits), many types of “healthcare providers” and services jumped to the forefront for these types of visits. Services like Teladoc, having been around a long time, started getting more notoriety for the virtual service they offer. It’s important to understand the differences between telehealth and virtual services and telemedicine appointments with your own doctor.
We often hear from patients interested in Direct Primary Care practices, like Direct Doctors, that they “have regular insurance, so why do I need this too?” We’ve reviewed the “why” in many prior blogs, but here is the “how” it works.
Over 95% of our patients have insurance. They still use it. If they have specialists to see, colonoscopies to undergo, meds to fill, or labs to get - they still use their insurance. Direct Doctors can send the order to the lab, refill your prescription at the pharmacy, or refer you to your chosen specialist (we don’t have to stick in the networks like some corporate PCPs) all through your insurance. This all feels just exactly like you’re used to with a fee for service PCP office. Your average physician’s office cannot accommodate the needs of the 2000+ patients that they have per doctor in the normal day. If the doctor is full or not in the office that day, they will often either recommend that you come in and see a non-physician practitioner or go to the local urgent care where you can walk-in anytime you need it.
At Direct Primary Care practices, like Direct Doctors, we do our best to be available to you when you need it. While we can’t guarantee 24/7 in-person access, we can be sure to get back to you when you have an urgent need. Our patients text, email and call us when they have an urgent concern and they hear back from their doctor directly within hours (and usually within minutes!). When scheduling allows and the need requires an in-person assessment or treatment, their doctor directly schedules them to come in for what they need. We’ve done a few blogs about health care pricing (medications, office/ER visits, etc). Another big health care cost hurdle that patients deal with quite often is the cost of labs or blood work. If you’re a patient with typical insurance, have you ever received a bill from a lab for several hundred dollars for “routine blood work?” You probably assumed insurance would “cover” everything because you pay for an expensive health insurance plan. Or maybe you’re a patient without insurance or a high deductible plan that has to pay for many costs before insurance even kicks in. Have you ever wondered why labs cost so much? Or why the typical primary care practice you were going to didn’t warn you about the costs or ask your financial situation to be sure you could pay for such costs? Most likely, the pricing you received on your bill didn’t look like this:
Every year we release a blog about the open enrollment season and things folks should think about when purchasing health insurance. Most of the information is consistent this year, though I’ve updated things a bit below:
Whether you purchase your insurance through the state, government, employer or directly from the vendors, this can be a daunting process. There are often many choices, with slight differences that are difficult to decipher. Beyond that, because price transparency is such an issue in healthcare, it is often hard to plan or budget for future costs when there is no way to find out how much these services actually cost! Below, I’ve tried to outline a couple tips while going through this process. Over the past few years, we’ve highlighted the savings of over $3000 in 2 years that the Smith family was able to keep on hand because of being members of our DPC practice at Direct Doctors. In 2016, we highlighted the following cost savings on medications:  Since then, we’ve continued to share our wholesale medication pricing with our patients. Some of the most common medication savings we pass on to patients are:
Because in RI doctors are able to wholesale order medications for their patients when clinically appropriate, we can cut out the pharmacy/insurance middle men and offer direct pricing to our patients at cost. This reflects a savings to patients, especially on chronic medications, that is not found in the typical primary care practice. These are just examples but we are always happy to help interested patients compare pricing to see if the addition of medication-cost-savings may tip the scale in favor of a DPC membership. Check us out at www.directdoctors.org for more info!  In past years we have visited the Smith Family, a typical working family of three looking to reduce their healthcare expenses through a membership with our Direct Primary Care practice, Direct Doctors. We looked at how they were able to save $1350 during their first year as members of Direct Doctors just by switching to a higher-deductible, lower-premium health insurance and joining the practice for their primary care.
We eliminated costs for their family by helping them keep their care in the primary care office setting. We decreased (in fact, eliminated) their need for specialist visits and handled their urgent issues in our office or via text/email/cell phone when necessary. In their second year as patients, they found additional savings benefits through reduced medication co-pays and laboratory co-pays. This is no mystery - labs and meds cost more when you use third parties. This is a common question in the Direct Primary Care world. Now that DPCs, like Direct Doctors, are popping up all over the place, patients want to know what options there are to pay the monthly fee (which is billed to patients directly rather than through insurance as in a typical practice).
Let’s start with the FSA - or flexible spending account. These accounts allow employees to put aside a certain amount of pre-tax dollars to be used on healthcare costs. FSAs are administered and run by various third parties. In our experience, whoever the third party administrator is will determine whether the FSA can be used to cover monthly fees. They allow doctor payments to be covered almost universally, but whether they allow you to set up a monthly direct debit varies from one to the other. For those who prefer not to do monthly fee coverage, they will often allow you to submit a few times a year to request a lump sum reimbursement for the fee you’ve paid up until that point as “doctors fees.” Bottom line - check with your FSA’s third party administrator on what they prefer! Patients of Direct Primary Care (DPC) practices, like Direct Doctors, have really come to love the ability to reach their doctor through modern technology. We’re all used to texting and emailing our friends and family - so, why is the traditional medical world so behind on using this form of communication?
There are a few main reasons that your doctor isn’t letting you text them: This is one of the more common questions we get from patients wondering why they’d pay a monthly fee to join our practice. Many patients “only go to the doctor once a year for a physical,” or “aren’t on any medications.” Others cannot fathom paying for primary care on a monthly basis when they are used to the slow, inefficient traditional primary care practices that are impossible to get in contact with.
However, we have many of these patients in our practice. They come to realize that direct primary care practices like Direct Doctors are beneficial for many reasons, even for generally healthy patients. For one thing, many patients realize that they probably use a physician more than they think. Whether it’s an urgent care visit for a sore throat, an ER visit for stitches, or just a simple medical question that required an in person visit at a traditional practice, patients often underestimate the amount they use the medical system, or would use it with a better overall experience. All of these can be handled at our practice, at no charge on top of the monthly fee, in a patient friendly and efficient manner. And that ER visit for a simple laceration repair most likely costs more than a year of membership to our practice. Like many DPC practices across the country, Direct Doctors offers more to our patients than the average fee-for-service (insurance based) primary care practice.
Some highlights include:
The process of getting an MRI for a patient used to involve two things - a doctor who wanted an MRI and a patient who needed an MRI. A doctor is trained for over 11 years (many specialists are trained even longer) to make the right decisions on behalf of patients. We use that knowledge and training to decide when an MRI makes sense for our particular patient’s situation.
However, in the past decade or two things have changed drastically and continues to become progressively more complex. Now getting an MRI involves:
 *Below is ongoing analysis and advisories of news and alerts related to COVID-19 (Coronavirus) from Lauren Hedde, DO and Mark Turshen, MD of Direct Doctors. This post will be continuously updated as news and advisories of this issue are disseminated.* 7/6/2020 - 1:10pm EST By: Lauren Hedde, DO Travel and quarantine: There is a required 14-day quarantine for anyone coming to Rhode Island from any state with 5% or greater positivity rate. As an exception to that rule, you will not have to quarantine if you have had a negative coronavirus test within the past 72 hours. If you are a Rhode Islander who travels to a place where cases are spiking, you should quarantine for 14 days. As an exception, you will be able to sign up for an asymptomatic test (if you don’t have symptoms) by going to portal.ri.gov. If you test negative, you won’t have to quarantine. For people visiting Rhode Island from out of state, RIDOH recommends They get tested for COVID-19 in their home state, if possible. However, people from out of state can find a place for asymptomatic testing on RIDOH’s website. The individual being tested, or their insurance, would be billed for the testing. Rhode Island is not offering free testing to out-of-state travelers at this time. If you receive a test after arriving in Rhode Island and get a negative result, you can stop quarantining." 6/18/2020 - 1:07pm EST By: Lauren Hedde, DO ASYMPTOMATIC TESTING Testing for patients WITHOUT symptoms will take place in the parking lots of: Stop & Shop Cranston: 275 Warwick Ave Stop & Shop Pawtucket: 368-398 Cottage St. Stop & Shop Providence: 850 Manton Ave. and 333 W. River St. Asymptomatic workers who can schedule tests include child care workers, barbers, cosmetologists, gym and exercise trainers, personal care services (nail technicians, massage therapists, tattoo artists, estheticians, cosmeticians, manicurists, body piercers, and tanning facility staff), public transit drivers, and restaurant workers. In addition, people who have recently attended a large protest or demonstration are encouraged to get tested. Eligible Rhode Islanders can schedule an asymptomatic test at one of the four Stop & Shop stores by visiting portal.ri.gov or calling 401-222-8022 Monday – Friday 8:30 a.m.- 4:30 p.m. SYMPTOMATIC TESTING People with COVID-19 symptoms will not be tested at these locations and should contact their primary care provider or respiratory clinic to schedule an appointment for testing. 6/12/2020 - 2:06pm EST By Lauren Hedde, DO Governor Raimondo released the state's new 3-pronged testing strategy: 1) Rapidly test every Rhode Islander that is symptomatic 2) Quickly react and deploy infection control for outbreaks within (4) hours 3) Create and expand early warning testing system by testing key groups of asymptomatic Rhode Islanders. A new "Early Warning Testing System" has been put in place, with an important focus on communities of color, encouraging first responders and employees of close-contact businesses, child care centers, and congregate care settings to schedule a free test at one of the Rhode Island National Guard sites (RIC and CCRI). The goal is to be testing 900 people per day that are asymptomatic. The free test can be scheduled online or by calling 401-222-8022. 5/5/2020 - 1:29pm EST By Lauren Hedde, DO These days we are getting many questions and requests about having COVID antibody testing done. A little background. Antibodies - to be clear - are the proteins formed by your body when you have had exposure to an illness. In this case, we are talking about sars-cov2 antibodies. There are two main types of antibodies to any given infection that we want you to be aware of - IgM and IgG. IgM usually forms early, within days of illness and then goes away fairly quickly, whereas IgG takes more time, usually weeks to develop but lasts a lifetime (or usually that is the case with lots of infections). Currently, lots of tests are coming out to test these antibodies, which in theory sounds like a great way to find out if your mysterious February cold was actually COVID! Unfortunately, it is not that simple. And at the moment, the message from the RI DOH, is to wait except in very rare cases where a patient has very straight forward COVID symptoms but two swabs have come back negative. I get that this is very frustrating to many patients who want to know if they "had it" already. So here is some more info on why! The accuracy of a test like this depends on how many people in a community have it. So, in a place like NYC where there were lots of people with the disease, the test is much more accurate. In a place like RI, where we don't think the prevalence has been as high, the results would be less accurate. Meaning, there is a much higher chance of false positives (patients who have a positive result of antibodies but never actually had COVID) and false negatives (patients who have a negative results of antibodies, but did actually have COVID). The more false results you have, the less accurate the test is and the harder it is to know how well results can be "trusted." The other issue is that the coronavirus, sars-cov2 which causes COVID, is one of 5 coronaviruses that circulate in the US and the tests may overlap and result positive for patients who have had one of the other strains, rather than the current sars-cov2 strain. All of the above means, patients could get a results of "I had COVID" and either have actually had a different coronavirus that does not give immunity to COVID or not actually have had it at all (false positive). If we were to test lots of patients who did not have a very clear COVID-like illness (fever, short of breath, chest pressure, cough), we would get lots more false positives. If those patients now feel comfortable ignoring social distancing or returning to activities that the governor suggest should be avoided, we would return to a spike of COVID activity, overwhelm our healthcare system, and infect lots more patients who may suffer greatly from this. Lastly, we have no idea how long the IgG antibody lasts, nor if it leads to longterm immunity. Folks in China and South Korea are now reporting "re-infection," which either means there is not longterm immunity for some patients, OR there is longterm immunity but those "positives" were false. 4/8/2020 - 4:15pm EST By Lauren Hedde, DO CONTACT LISTS - The Governor is suggesting all Rhode Islanders keep lists of contacts: where you went, who you saw in close contact, what you did. Track this, for example in the notes on your phone, and reference it if you test positive for COVID. This will help the Department of Health track cases more easily and help stop the spread! MASKS - The Governor and CDC are recommending everyone who leaves the house, especially to go to a store for essentials, wear a cloth covering to minimize potential for asymptomatic or mildly symptomatic spread (think, you probably just have allergies but it's COVID and you didn't know it!). - Wearing these prevents YOU from spreading it to others, if you were to have it unknowingly. ACCESS TO MENTAL HEALTH SERVICES IN RI - Adults call 401-414-LINK - For children, call 855-543-5465 RETURN TO WORK * this is updated information * - The RI DOH is now requiring patients be without fever for 3 days and have resolution of all other symptoms as well as be at least 7 days from the start of symptoms. - For folks who have tested positive for COVID, there is another testing option for return to work. Reach out to your PCP if this is you and you are unsure. TREATMENT We've gotten lots of questions about what meds should be and are being prescribed for COVID treatment as well as what meds should be stopped if you test positive. - ACEi/ARBS - media have been suggesting these medications (i.e. lisinopril, losartan, etc). may cause worse outcomes for patients taking them with COVID. - Currently the DOH and American Heart Association say do not discontinue these meds now or if someone becomes ill while taking them. - NSAIDS - there is no hard data that ibuprofen etc use does worsen COVID outcomes. RI DOH says to try tylenol, etc first and use NSAIDs judiciously for now if sick with cough/fever or proven COVID. - REMDESIVIR - this investigational IV drug is given only in hospitals. RI hospitals do have the option to use this experimentally. - HYDROXYCHLOROQUINE (Plaquenil) - this oral anti-malarial and autoimmune drug has shown some un-researched potential for treating patients with COVID. Currently there is no actual data to support this. We are all waiting to learn more at the moment. Both chloroquine and hydroxychloroquine can cause heart arrhythmias but fairly uncommon for short term use. RI doctors can now prescribe this off label for COVID-19 confirmed cases for patients who are more than moderately ill (i.e. to try to keep someone who is quite sick from needing the hospital) but not for mild to moderate self-limited cases of patients doing well on their own at home. This is especially an option for nursing home patients. SYMPTOM UPDATE - The loss of smell and taste does seem to be a common feature in COVID (though can be caused by lots of other viruses) but worth noting on the list of reasons to test if a patient has this plus other more well known COVID-19 symptoms. CVS RAPID TESTING - Remains available only for specific populations so contact your PCP for more information. 4/6/2020 - 3:42pm EST By Lauren Hedde, DO CVS Rapid Testing: - Only certain patients will qualify for rapid testing through CVS right now. - If you have no PCP, you can consider filling out this form to see if you qualify for it. - As of today, even if you qualify, there are no times available at the Twin River location for this test. Obviously, this will likely change each day as new dates/times are added. - If you have talked to your PCP, and they advise testing, CVS will honor that and you can skip the questionnaire and go straight to signing up for a time slot (once they become available). - Your PCP can still order the usual test (which takes 3-4 days for results) at one of the drive through locations throughout the state for the next day (which are currently available now). - As always, if you're not sure which route to go or if you aren't even sure you need testing, reach out to your PCP for advice! 4/2/2020 - 1:46pm EST By Mark Turshen, MD As of today, COVID testing has been extended to any patients with symptoms here in Rhode Island. Please note, this means you must be currently symptomatic to warrant testing. This is not testing to see if you previously had the virus. The symptoms of COVID-19 include any of these symptoms (some patients have only 1-2 of these and may be mild):
All patients should still contact their primary care physician if they do experience symptoms so they can help coordinate and order the test. There are 3 drive through testing sites now set up throughout the state, along with respiratory clinics for those who need exams and testing. Drive through testing can only be set up and ordered by your PCP. Respiratory clinic visits should be discussed with your PCP first as well. We often stress the importance of having a good PCP, and especially one you have a good relationship with and can contact easily. The current situation is certainly highlighting this point. 4/1/2020 - 2:52pm EST By Lauren Hedde, DO Who is at Risk? - Everyone is considered at risk for COVID now. - We have widespread community transmission throughout the United States. - The only way to lower your risk of contracting COVID now is to avoid close contact with other people. Stay home as much as possible. Quarantining - Anyone who you have close contact within 6 feet for a significant amount of time (i.e. those you live with), is considered a contact. If you test positive for COVID OR even if your doctor just thinks your symptoms are COVID-like, then your contacts need to quarantine for 14 days. - Anyone who had direct contact with a COVID+ patient, as early as two days before symptoms, must quarantine as well. Testing - More testing is coming soon for almost everyone who has symptoms - As we learn more about this, we will update you. It will still likely require a check-in with your doctor and order for the test. Advanced Directives - This is never an easy topic, but now more than ever, it is a good time to be sure your family knows your wishes should you become very ill. - Having a living will, power of attorney, and perhaps a MOLST. If you have questions about any of these your PCP can help! 3/31/2020 - 12:05pm EST By Mark Turshen, MD Given the changing guidelines on testing and some confusion around recent statements made by Governor Raimondo, we wanted to update everyone on who is currently eligible for COVID testing. This includes symptomatic patients only in the following patient categories: - hospitalized - nursing home/assisted living residents - healthcare workers including EMS - first responders (fire fighters, police officers, etc) - 65 years of age and older - those with underlying conditions placing them at higher risk (please talk to your doctor about whether this is you, conditions placing people at higher risk do not necessarily include all medical conditions) For patients who did not fit into one of the above categories with mild illnesses, the recommendations are still to stay at home, recover and not have testing done. 3/30/2020 - 2:17pm EST By Lauren Hedde, DO Can anyone get a COVID test who wants it now? No. You must first call your PCP and have an evaluation about your symptoms, risk factors, and work. If you are in the higher risk categories or are considered an essential worker your PCP can order the test and arrange a drive thru testing for you. If you are not considered in the high risk group, you will not have a test ordered for you and still will be urged to stay home and weather it without testing or visiting a clinic. If your symptoms are unclear, your PCP can help direct you to a respiratory clinic for a full evaluation, but that must be done with a call-ahead as well. Only patients with an order for COVID testing from a physician/NP/PA will get tested. Can I go to urgent care if I feel sick? No-one can just show up right now to any location without a visit being called in ahead of time and planned. Please call your PCP first. If you don't have a PCP, you may consider finding one now or calling the urgent care to see if they will help triage you over the phone. If I have COVID symptoms and don't get tested, do I have to quarantine? Yes! Many patients will never get the test but will have the diagnosis based on symptoms alone. Please do as anyone would with a positive test and stay home. This means isolating from all possible contacts and certainly not going out for at least 7 days since onset of symptoms and at least 3 days without a fever (and without any fever reducing meds). Your personal contacts should stay home in a 14 day quarantine until it is clear they do not have symptoms. 3/26/2020 - 2:38pm EST By: Lauren Hedde, DO
3/24/2020 - 11:17am EST By: Mark Turshen, MD - Despite all the recent hype around the use of both Hydroxychloroquine (Plaquenil) and Azithromycin in the treatment of COVID-19, there is currently not enough evidence that any governing bodies are recommending these routinely, either for outpatient treatment OR prevention. Unfortunately, because of the hype, it has actually become difficult for patients routinely on Hydroxychloroquine, for things like lupus and other autoimmune disorders, to get their medications. So please keep this in mind when thinking about "prevention," and when stocking up on items that others may need. - For all patients who routinely get seasonal allergies in the spring, this would be a great time to start your preventive measures. Whether that includes natural remedies, flonase, claritin/zyrtec/allegra, etc, getting a head start on symptom control may help to prevent a large number of patients getting allergy symptoms that could be confused with viral symptoms over the next month or so! - As always, things are changing rapidly so we will continue to try to keep you updated in real time. 3/20/2020 - 11:48am EST By: Mark Turshen, MD - The CDC and RI Department of Health continue to recommend all patients with mild symptoms simply stay home and recover. Given the limited tests available, they are prioritizing testing for severely ill and/or high risk patients. Anyone with symptoms should stay home to rest, hydrate, use over the counter remedies for specific symptoms and help to reduce the spread. - For those currently still working outside the home with symptoms, the return to work policy is currently: * at least 72 hours fever free without the use of medications, AND * symptom free from respiratory symptoms, including resolution of cough, AND * at least 7 days since the start of any symptoms - While COVID is greatly affecting our older patients and folks with chronic illnesses, young and healthy patients are also having complications. We implore our younger population to heed the warnings and advice on social distancing. - If you have any N95 masks or other PPE (personal protective equipment), please donate them to the department of health ASAP. - As you've seen the last few days, things are changing rapidly so we will do our best to continue to update you in real time. 3/16/2020 - 9:56am EST By Lauren Hedde, DO Why You and Everyone you know Should Social Distance NOW Two weeks ago I did not know what “social distancing” was. Today I can’t look at facebook or turn on the news without hearing it. Here’s my perspective as a physician on what it is and what to do NOW. Facts we know about COVID-19:
If you social distance, you are:
When you social distance effectively, you slow the spread by asymptomatic viral carries (kids, young healthy adults) to those at higher risk of serious illness. When you prevent those higher risk patients from getting sick, you slow the curve. But what is all this talk about flattening the curve? The graph below says it all. If we can slow the spread, we can slow the pace of folks getting sick (i.e. the blue curve showing the pace of illness spreading with use of protective measures - i.e. social distancing). If we do not listen to our local government and medical community, and we keep sharing space with others, we will spread this much faster (i.e. at the pace it happened in Italy). If we spread this faster, the curve will look like the red one. It will quickly reach a pace where the 10-15% of those who get sick that need hospital and ICU care will overwhelm the amount of beds, intensive care personnel, and ventilators we have in RI and in the US. This is a dire situation - the oldest and sickest will not get the ventilators because they will be rationed to those with the “best chance” of recovery. It will put more strain on doctors, nurses and respiratory therapists, who are at highest risk of illness from exposures. Many of those folks who care for our sickest patients will get sick and be unable to help. The sooner we all realize that the inconveniences of social distancing will prevent a complete overwhelm of our healthcare system, the sooner we can get the curve to start flattening. As you can see here, we’re in the “exponential growth phase.” We are tracking along countries like Italy and South Korea where social distancing was not enacted quickly. If we can change that curve, and enact rapid social distancing, we can have better success as has happened in Japan and Singapore. 3/14/2020 - 3:26pm EST By: Lauren Hedde, DO Blue Cross Blue Shield of RI has temporarily changed their policy so members can refill prescriptions earlier than the standard 30 days. This applies to all medications except a few, such as opioids. For medications that treat chronic conditions, members may have access to a 90-day refill. Upon request, members can obtain a six-month supply of their prescription. 3/12/2020 - 10:34am EST By: Mark Turshen, MD As we have been fielding many questions and visit requests related to concern for coronarvirus (COVID-19), we wanted to reach out with some information for some common concerns. - What does it cause? COVID-19 causes a spectrum of illness from a mildly symptomatic cold to a severe febrile respiratory illness (breathing trouble, high fever). Older patients and those with known medical co-morbidities are considered at higher risk of complex infections (however we don't have enough info to know who exactly those patients are). - What should I do if I know I have been exposed? You should call us (or your own PCP) and let us know and we will contact the DOH and communicate a plan with you. You should stay home. The CDC defines exposure as close contact with someone with a positive test for COVID - "being within approximately 6 feet of a COVID-19 case for a prolonged period of time; this can occur while caring for, living with, visiting or sharing healthcare waiting area or room." - What should I do if I have mild to moderate symptoms of a cold/flu? You should stay home. We are happy to chat remotely with our patients and advise you on symptomatic treatment options but we will not suggest you come in for a visit. The CDC wants patients to stay home (out of work, school, and offices) unless severely ill (see below) to prevent other exposures. We do not have protective masks/gear here because they have sold out and are being kept for the healthcare workers who really need them at the hospitals. If you are not a Direct Doctors patient, contact your PCP for more information. - What should I do if I have severe symptoms (difficulty breathing) of a cold/flu? Obviously call 911 first for emergencies. Otherwise, please reach out to us directly (or your own PCP) and let us know what symptoms you are experiencing. We can help guide you for testing and treatment at a local emergency room where they have the correct triage and protective equipment procedures in place. We will call them first to tell them you are coming if we both agree that is the right step. - Where do I get tested for COVID and do I need testing? At the moment you will only be tested for COVID if you have severe illness OR known exposure to COVID + are now having symptoms. Known exposures can include travel to Japan, Iran, China, South Korea, or Italy within the 2 weeks prior to symptom development. This test is not being done in our office. We will discuss with you where to go if needed. - If I have symptoms, how do I know if they are severe? Please reach out to us first (or your own PCP) so we can help identify via text/email/call if your symptoms are severe or mild/moderate. Severe will include breathing difficulties like shortness of breath. - Should I be afraid of COVID? This is a virus caused by a coronavirus. We have other viruses like the common cold which are the same subtype of virus. Most patients will have a mildly symptomatic cold, which is nothing to be afraid of. However, if you are older and/or have medical conditions, it is probably wise to stay home more than normal, avoid big/crowded events, and continue good hand-washing practices to keep yourself and your family healthy. As always, if you are a Direct Doctors patient we are here to help answer your questions! - Where do I get more info if I want it? We will do our best to update you on any new guidance but we suggest focusing on the CDC and RIDOH websites for your information.  The other night I was chatting with my husband (who is a primary care doc in “the system”) about the differences between what I do and what he does. We realized, the biggest differentiator between how we practice has to do with what incentivizes us. We can all pretend we don’t get swayed by incentives, but if we put that aside - here is the real difference.
At a traditional fee-for-service practice, doctors have to bring you into the office in order to get paid. In other words, if you aren’t seen for a visit, they cannot send a bill to your insurance company, so they cannot bring money into their practice. For example, any portal messages you send are not billable if they spend time responding. Currently, phone calls aren’t able to be billed either. Ultimately, they are incentivized to keep bringing you into the office. Do healthy people want to go to their doctor’s office all the time? Most do not. Not that traditional FFS doctors are trying to keep you unwell, but you can see where the incentive lies in terms of visits. The other night I was chatting with my husband (who is a primary care doc in “the system”) about the differences between what I do and what he does. We realized, the biggest differentiator between how we practice has to do with what incentivizes us. We can all pretend we don’t get swayed by incentives, but if we put that aside - here is the real difference.
At a traditional fee-for-service practice, doctors have to bring you into the office in order to get paid. In other words, if you aren’t seen for a visit, they cannot send a bill to your insurance company, so they cannot bring money into their practice. For example, any portal messages you send are not billable if they spend time responding. Currently, phone calls aren’t able to be billed either. Ultimately, they are incentivized to keep bringing you into the office. Do healthy people want to go to their doctor’s office all the time? Most do not. Not that traditional FFS doctors are trying to keep you unwell, but you can see where the incentive lies in terms of visits. The average healthcare insurance CEO makes millions in bonuses. The average family in RI makes $63,870. Yet insurance companies have multiple roadblocks in place to decrease what they cover for the average patient.
As primary care doctors, whether we practice in our model of direct care at Direct Doctors (monthly membership), or a traditional fee for service model (you pay per visit, usually billed to insurance and then a copay requested from you), all PCPs have to jump through insurance company hoops. For example, if I see a patient of mine who has injured their knee and it seems pretty certain to me they have torn something that likely requires surgery (and won’t get better with just therapy and ibuprofen), my job as the physician is to recommend and order for an MRI. If a patient does not have insurance, or has a healthshare like Liberty, I can send that order directly to the imaging facility and the patient can pay the cash price, which in our experience is from $400-700. We all know and admit there are a lot of problems in U.S. Healthcare. It may not always be clear what they actually are, or better said, what the actual root causes are. It’s clear to many that when you call to see your doctor, you can’t get in quickly; when you look for a new PCP taking patients, you wait 6 months for your new visit; when you want to see the doctor you signed up for, you see a PA instead; when you want to talk to your physician, an RN or MA gets on the phone instead.
But why is that? What has happened to the era of house calls, general practitioners who cared for your whole family and swung by when the kids were home with Scarlet Fever? Why don’t doctors take care of you like they used to? Every year we release a blog about the open enrollment season and things folks should think about when purchasing health insurance. Most of the information is consistent this year, though I’ve updated things a bit below:
Whether you purchase your insurance through the state, government, employer or directly from the vendors, this can be a daunting process. There are often many choices, with slight differences that are difficult to decipher. Beyond that, because price transparency is such an issue in healthcare, it is often hard to plan or budget for future costs when there is no way to find out how much these services actually cost! Below, I’ve tried to outline a couple tips while going through this process. Nothing is free!!: Many patients get a large portion of their health insurance paid for by a third party (employer, government, etc). This creates the notion that health care is cheap or free in certain situations. Please remember that although you may not pay much in monthly premiums or out of pocket costs for your insurance, your employer is likely paying an exorbitant amount for health care services you may not even use. This cost has gone up considerably in the last few years When some people hear about Direct Primary Care, they automatically think of concierge medicine and assume they cannot afford it. DPC skeptics will tout that membership based care is only for the uber wealthy and will leave those well off behind. However, did you know that only 3% of Direct Primary Care patients would classify as "Upper Middle Class" or above nationally.
|
AuthorLauren Hedde, DO; James Hedde, DO and Mark Turshen, MD are Family Physicians and Co- Founders of Direct Doctors, Inc. a Direct Primary Care Practice. Archives
October 2026
Categories |
 RSS Feed